A therapeutic target has been identified that brings us closer to the goal of preventing brain metastases and avoiding relapses
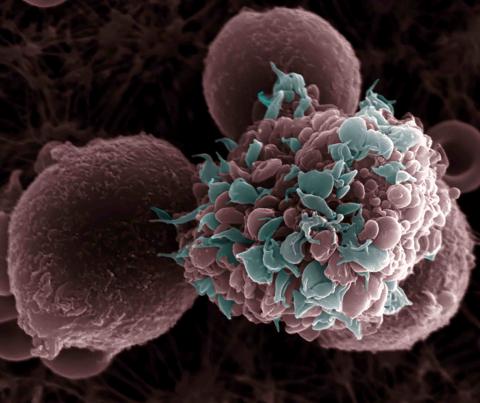
A team of Spanish researchers has investigated the early stages of metastatic cells taking hold in target organs and has discovered that there is a transitional stage during which these ‘metastatic seeds’ are particularly vulnerable. They have also demonstrated in mice and in human samples that these micrometastases can be eliminated using three drugs, two of which are already approved for other indications. The study is published in the journal Cancer Cell.
Jordi Bruna - metástasis CNIO
Jordi Bruna Escuer
Coordinator of the Neuro-oncology Unit of the Bellvitge Biomedical Research Institute (IDIBELL) and researcher of the Neuroplasticity and Regeneration Group of the Autonomous University of Barcelona
It is a very good piece of work that must have required a great deal of effort – as is partly reflected in the number of authors – and has drawn on vast resources to underpin the entire experimental programme. I believe it is worth reporting. I think its preclinical conclusions are relevant, despite potential criticisms that might be levelled at it (though it has already undergone peer review in a rigorous journal). What is not entirely clear to me is its clinical applicability or how to frame it within current therapeutic contexts.
Points I do not like:
- The distinction between dormant cells and pre-metastatic cells is unclear, and the action of the described pathway and its modification in the former is uncertain. This consideration is important when determining the duration of treatment; whether they lose their quiescence and when they do so will depend on this pathway.
- Related to this, a biological window for treatment is not the same as an identifiable clinical window.
- I am not convinced by the post-surgical application; post-surgical radiotherapy to prevent relapse has already been thoroughly proven and is well established. I do not see any immediate utility or application for this finding in this context, despite it being one of the study’s models.
- We must not forget that systemic treatments carry a risk of toxicity, particularly in situations where the patient may be paucisymptomatic or asymptomatic due to their underlying condition. Furthermore, it remains to be seen whether the treatment is tolerable if it is to be combined with another treatment for the primary tumour; therefore, when and how to prevent such toxicity with this new approach is important and, obviously, given the mechanistic nature of this research, has not been addressed.
- There is always the risk of model extrapolation (all of which are more or less artefactual), but there is pseudo-validation using a patient sample. Despite this, the finding is worth exploring clinically, provided that the timing and circumstances are clearly defined.
- It should be made clear in the article that the results come from experimental models and human samples cultured in the laboratory, not from treated patients. False expectations must not be raised among current patients; significant clinical development remains before any potential application. The possibility of preventing metastasis or recurrence remains a clinical hypothesis requiring trials, not a certainty.
- In this regard, I would avoid exaggerated claims such as that micrometastases can be eliminated or that the drugs have eradicated them. The experiments show a reduction in the metastatic burden, but do not prove complete and lasting eradication. I would use a phrase such as ‘they reduce the viability or progression of micrometastases in experimental models’.
Pilar Sánchez - metástasis CNIO
Pilar Sánchez Gómez
Senior Researcher at the Carlos III Health Institute, Head of the Neuro-oncology Unit at the Chronic Diseases Research Unit (UFIEC-ISCIII)
Does the article accurately reflect the study?
“It’s fairly accurate, although there are a couple of sentences that strike me as overstated, particularly with regard to the therapeutic implications.”
Is it a high-quality study? Do the data support the conclusions?
“It’s an excellent piece of work that addresses a biological question that is very difficult to tackle. The authors draw on a wide variety of techniques and samples, both in vitro and in vivo, from both animal models and human samples. The level of coordination achieved by the PI [principal investigator] across several clinical centres to obtain these samples is remarkable, particularly the autopsy cohort, which is especially valuable for this study. The data provide strong support for the existence of a ‘pause’ that helps metastatic cells survive in the brain. I find the findings robust regarding the mechanism controlling this pause in metastatic cells and the potential pharmacological and genetic modulators. I find the parallel drawn with the mechanism of tumour reactivation following surgical removal somewhat weaker; I believe that aspect requires further studies to be confirmed.”
How does this fit in with existing evidence?
“Both Dr Valiente’s group and other groups had already described the initial mechanisms of extravasation and the onset of metastasis, although this study now goes a step further and describes an intermediate step which, to my knowledge, had not previously been described.”
Confounding factors and limitations
“The authors honestly describe some of their scientific and technical limitations in the discussion. The main one would be the translational application, as there are no biomarkers that allow the detection of patients with micrometastases. Apart from those they describe, it strikes me as a limitation that the study begins with samples from patients with the same tumour type, and that the tissues from the British cohort are all from lung cancer. Given that these samples form the basis of the work, this poses a risk to its extrapolation to other types of metastasis, although it is true that they also carry out several experiments on samples from the RENACE cohort, which do indeed comprise various tumour types. Another significant limitation is that the two main molecular targets described in detail, MYC and MXD4, have no known pharmacological inhibitors; the authors therefore suggest downstream mechanisms that could be modulated by these proteins. They present results consistent with this line of thinking, but this is perhaps the weakest aspect from a mechanistic perspective.”
Implications for real-world practice
“I agree with Dr Valiente that this study lays the foundations for avenues of research aimed at halting micrometastases and, therefore, preventing them from developing into aggressive tumours in the brain. As it is inconceivable to treat all cancer patients with drugs preventively, we would need, in parallel, to characterise biomarkers (in blood or radiological) that can distinguish the early onset of micrometastases. Furthermore, further research is needed to determine whether this mechanism applies to tumour growth following surgery. It is true that such an application is more feasible in the short to medium term, but in my opinion, it requires more thorough validation.
Another implication that the authors do not explore is that this mechanism might also be relevant to understanding the resistance of these micrometastases to the stress induced by radiotherapy, which patients receive following surgery.
The study opens up a promising avenue, but it does not yet enable the prevention of metastases in patients. To achieve this, we would first need to identify those with micrometastases and validate the efficacy and safety of the treatments. It would also be interesting to investigate whether this pause influences their response to radiotherapy.”
García-Gómez et al.
- Research article
- Peer reviewed